 English
 Français
 Deutsch
 Русский
 Italiano
 Español
 Português


Candidates for knee stem cell treatment may include patients with osteoarthritis, meniscal tears, ligament injuries, or cartilage damage who are looking for non-surgical management of pain and improved function. The therapy is designed to treat the underlying problems in the knee joint stem cell therapy in order to relieve symptoms and improve mobility. It is best suited to those who are not yet at the end stage of their disease and wish to avoid or postpone surgery. Certain patient and treatment history characteristics can be suggestive of the possible benefit from stem cell therapy. An ideal candidate would have early or moderate degenerative changes in the knee with persistent pain unresponsive to more conventional treatments; such candidates for knee stem cell therapy would typically have requested an autologous therapy using their own cells but could use a pooled allogeneic product.
Acute or chronic infection, uncontrolled systemic disease, and recent surgery in the knee are contraindications. These limitations are not absolute but require some extra attention. Shared decision-making is part of this process; pre-treatment counselling must inform about expected outcomes, risks, and benefits to ensure informed consent as well as realistic expectations.
Knee Stem Cell Treatment
Ideal candidates for knee stem cell therapy have early to moderately severe degenerative changes in the knee and who have not had adequate relief of symptoms with conventional therapy. Activity-related pain or pain during daily activities that can reasonably be expected to improve in the short to medium term with a stem cell injection may be considered as indications for candidacy. Active infections, systemic disease, or recent surgery in the knee are contraindications to this procedure.
The decision on treatment is complex and should involve discussion with a clinician who can help balance potential benefits and risks based on the available data. A carefully crafted informed consent process is essential because any decision regarding a stem cell injection should be tempered by realistic expectations. Responses to stem cell therapy are heterogeneous; uncertainty still exists about the optimal patient population for this intervention. It holds promise-that is pain reduction, function improvement, and healing promotion-in appropriately selected patients.
What conditions can stem cell therapy help with in the knee?
The biological properties may be suitable for treating degenerative stem cell therapy for knee osteoarthritis, as well as other conditions involving focal stem cell treatment for cartilage damage, meniscal tears, and anterior cruciate ligament injury. There is increasing evidence supporting this diagnosis for which application is warranted based on regenerative medicine for knee pain principles.
What effect can patients expect during and after treatment?
Most patients want to know about the treatment itself and what they can expect to experience when considering stem cell therapy for knee conditions. Like all medical treatments, these procedures have an associated preparatory process and recovery is key to the outcome. The application of regenerative medicine for knee pain should follow a detailed analysis of the patient's pathological condition, which includes joint degeneration severity and stage, comorbidities that could influence healing and outcomes, as well as patient expectations and goals.
All patients should be aware of the possible benefits and limitations of these therapies. Regenerative approaches should ideally be applied when conservative treatments have failed or where surgery is not an option due to advanced age or other medical conditions; however, they are not indicated in patients with significant meniscal tears, ligamentous instability, or joint deformity requiring corrective surgery. These are patients who are warned that they may deteriorate further if they do not respond adequately and quickly to the treatment. In such cases, the decision should be driven by clinical risk-benefit assessment and shared decision-making with the patient.
An evaluation process guides the decision if a patient is indicated for stem cell therapy of knee pathology. An open dialogue regarding the injury; prior treatments and their results; clinical examination; imaging studies; and the presence of comorbid conditions that may increase risk in complications or affect outcome must all be considered. Key elements are described below in detail. A thorough review of clinical history and results from previous treatments is mandatory. Patients who have experienced some short-term relief after corticosteroid or hyaluronic acid injections might be more likely to respond positively according to this algorithm's rationale.
Standard imaging studies demonstrating the presence as well as the severity of osteoarthritis should be available. An MRI is not necessary at this point but could be requested by the attending physician if history raises suspicion for meniscal injury or other internal derangements based on clinical findings; however, it would help complete assessment. A risk assessment must clarify whether there exists any active infection, comorbid systemic illnesses, or other medical/surgical issues that would increase complication risks.
Risk assessment and outcome monitoring are usually carried out using validated PRO measures specific for joint pathology. Quality-of-life data and work-loss data may also be collected; these, together with clinical examination findings are considered in deciding on candidacy for any type of knee therapy. The monetary cost of therapy is an important factor, as well as its cost–benefit ratio from a clinical perspective. The decision-making process involves a combination of clinical experience with several consensus statements, clinical guidelines, and top-level knee-focused publications in regenerative medicine.
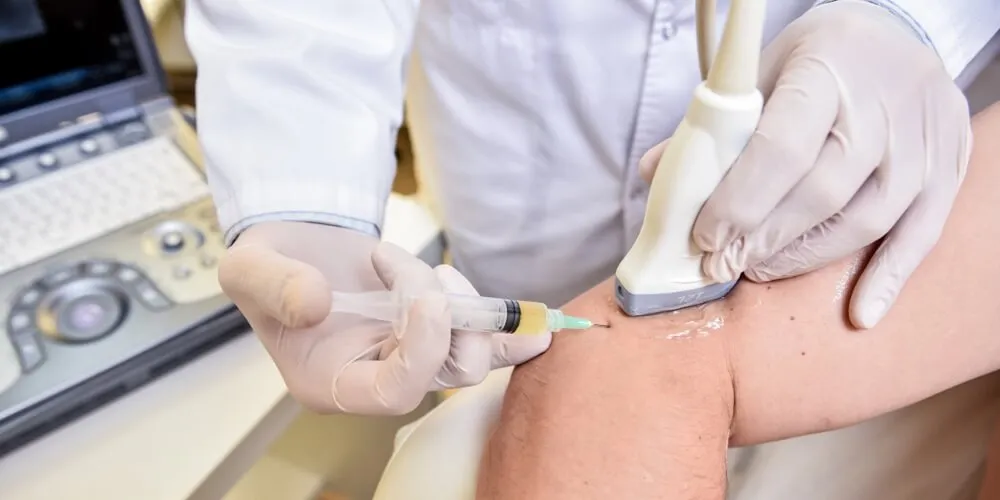
What are the risks and limitations associated with stem cell therapy for knee pathology?
Stem cell therapy for knee pathology can have risks, limitations in outcome, or both. Complications can result from adverse events common to any medical procedure as well as specific dangers relating to stem cell treatment. Suboptimal improvement might occur because of incomplete degeneration of target tissues, biological limitations, or selection protocols based on inadequate clinical evidence.
Like any procedure, side effects can occur, but serious problems seem rare. There is a risk of postoperative infection because it is an invasive procedure. Attempts at regeneration with stem cells might cause some discomfort and occasionally necessitate analgesics. Rates of adverse events or failure to improve vary widely; very few might remain unhelped in some studies while almost all need another intervention in others. Moreover, current evidence may not fully guide selection decisions. It is easy to overlook how crucial scientific evidence supports the concept when the notion of regeneration through cell-based therapies is so attractive and optimistic.
These considerations might impede proper patient selection, particularly for off-label use of stem cell therapy. Regulatory bodies as well as medical societies have increasingly called for responsible clinical use of investigational biologic products together with evidence-based protocols and clinical guidance. Clinical evidence in regenerative medicine for knee pain has recently matured to begin supporting clinical indications and contraindications for knee stem cell therapy. Therefore, choosing an appropriate medical center and experienced physician is still highly important.
What are the alternatives to knee stem cell therapy?
Non-cellular modalities readily come to mind when one thinks about treating degeneration and pain of the knee. Physical therapy plus rehabilitation should be emphasized; adding a weight loss program if indicated would also be very helpful. Corticosteroid or hyaluronic acid injections can now afford some symptomatic relief by their intra-articular application. Analgesics such as acetaminophen or oral anti-inflammatories may help too, while débridement of any meniscal pathology would certainly offer short-term relief.
Surgery is the other main option. For knees with degeneration, bracing might be a good reason; meniscectomy would be the next logical surgical step; then, osteotomy and finally arthroplasty should come into play. Of course, surgical techniques have advanced a lot in the last ten years. New surgical options in young patients, such as stem cell treatment for cartilage damage resurfacing, distal meniscal allograft transplantation, and biological augmentation of osteoarthritic joints, aim to restore knee function at early stages of degeneration. Stem cell therapy for knee degeneration would be an appealing treatment if it brought lasting relief from symptoms; at present, physiological changes appear less straightforward; hence, stem cell therapy is an option when one finds a symptomatic joint where other non-surgical or surgical interventions have failed.
Conclusion: Is stem cell therapy for knee problems right for you?
Knee stem cell therapy plays a role in managing select patients. Retrospective data are promising, and controlled clinical trials continue to unfold. There are risks and limitations, but many patients gain significant symptom relief with functional improvement. Matching therapy to candidate factors and individual treatment goals is best achieved through careful assessment.
The decision to go ahead with stem cell therapy should be made after informed consent and discussion of patient characteristics, goals, expected response, potential risks, and other treatment options. Not all patients with knee pain will be suitable candidates for knee stem cell therapy as described above. The choice is eventually based on the particular patient’s situation and an individualized plan for that patient. A physician interested in regenerative medicine for knee pain should be consulted so that recommendations can be made based on the specific condition and requirements at any time.
Stem cell therapy for knee pain should also be placed within the context of the entire multidisciplinary care model. Regenerative techniques must only make up part of the options considered when non-surgical treatment is being thought about. Other non-operative strategies such as physical therapy, weight management, bracing, injections, and medications may go hand in hand with regenerative approaches. Stem cell therapy may further prove its effectiveness through imaging studies and validated patient-reported outcomes.